
How the radar measures, how it was validated, what is cleared, what is published, and what we still do not have. Peer-reviewed work, regulator records and independent certification are labelled as such. So is our own analysis.
The sensor is an impulse-radio ultra-wideband radar. It sends very short pulses between 6.5 and 8.5 gigahertz, centred near 7.3, and listens for what comes back. A chest rising with each breath and moving with each heartbeat changes the echo in a way the sensor can read.
A centimetre-wave radar, not millimetre-wave. Longer waves pass through bedding, clothing, wood and thin glass, and are far less disturbed by a fold in a duvet or a change of sleeping position. They do not pass through concrete or metal.
Heart rate, breathing rate, the breathing waveform, movement and presence are all worked out on the sensor's own processor. No internet connection is needed to take a measurement. Nothing is recorded that could identify a face or a voice: there is no camera and no microphone.
Heart rate and breathing are read while the person is still, and a reading takes at least 30 seconds of stillness. Every reading carries a confidence value from 0 to 100; readings below 80 are discarded rather than shown.
Heart rate to 3 m. Breathing to 7 m. Movement to 9.7 m. Field of view about 130 degrees. Range resolution about 1 cm.
Less than −41.3 dBm per MHz, the indoor ultra-wideband limit (FCC 47 CFR Part 15, EN 302 065, RSS-220). Total radiated power is on the order of 0.1 milliwatt, hundreds of times lower than a typical home Wi-Fi router.
Presence (occupied or vacant), resting heart rate, resting breathing rate, the breathing waveform, and a movement measure. The same output on every product built on this radar.
Power draw about 800 mW from USB. Operates from −40 to +85 °C. Two sensors in one room do not interfere if they are more than about 30 cm apart. Onboard processor: Cortex-M7.
Power draw is what the sensor consumes from the plug. Transmit power is what it radiates into the room. They are different numbers, and the second is the one that matters for exposure.
Accuracy means agreement with a clinical reference. The studies below compared this radar with a physician counting breaths, with electrocardiography for the pulse, and with full-night polysomnography. The figure they report is an intraclass correlation coefficient, where 1.0 is perfect agreement and anything above about 0.75 is usually called excellent.
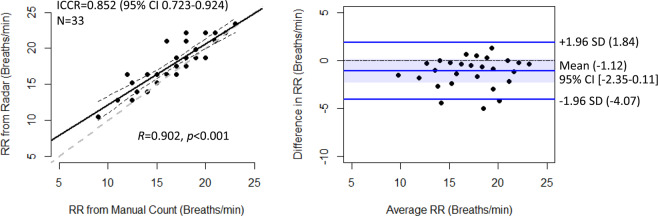
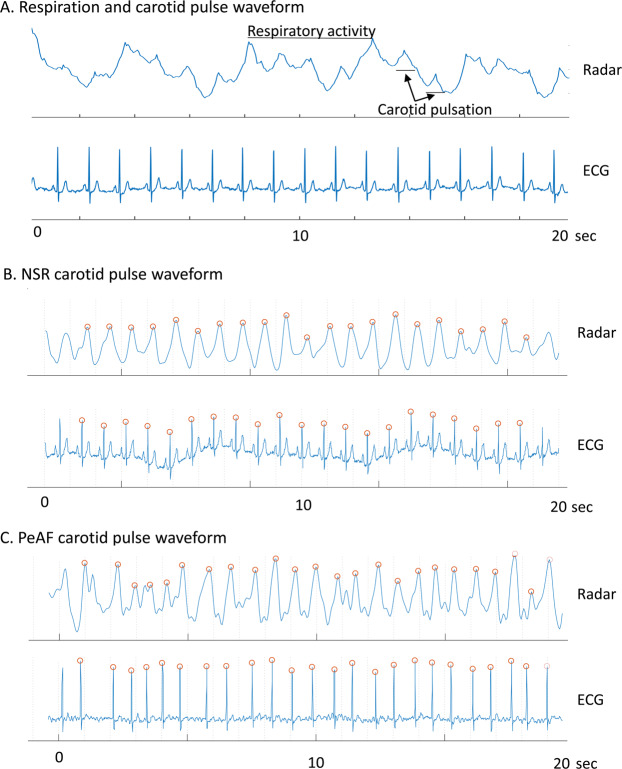
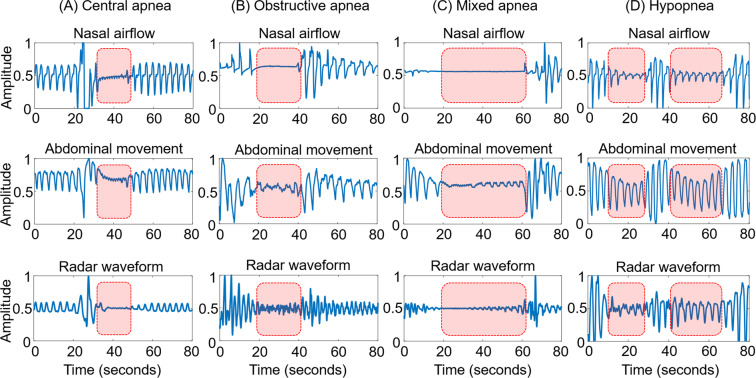
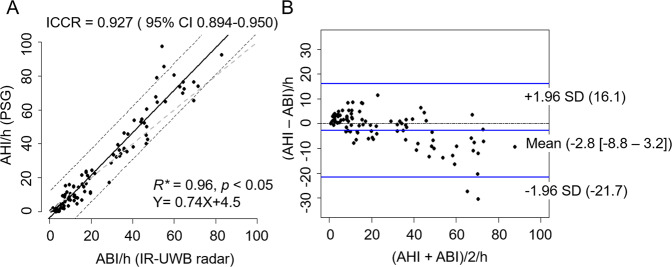
Figures are reproduced from open-access articles published under the Creative Commons Attribution 4.0 licence. Click a figure to open it at full size, or the citation to open the paper.
Each was a supervised session or a single night in a laboratory. None reports accuracy over months of unsupervised home use. Nobody's does, in this category, and we will not pretend otherwise.
Kardian products compare each night with your own recent nights. A one-beat difference on a single reading matters far less than a drift over several days, which is what care teams act on.
These studies were run on the impulse-radio UWB radar developed by our co-founder's laboratory, the technology behind the cleared XK300 and XK300 Essence. Kardian Somily is a separate wellness product built on the same underlying technology; it is not the cleared device and makes no claim to be equivalent to it. But they date from 2019 and 2020 and used research set-ups, with the sensor close to the person. The signal processing has been revised many times since. The current product is what the annual bench check against a reference monitor measures.
Most people who ask us about sleep already wear a smart ring, and we are compared with rings more than with anything else. So here is the honest comparison: what a ring does that we do not, what we do that a ring cannot, and why the two sit well together. We compare only where the same thing is being measured against the same kind of reference.
A ring estimates breathing from the pulse in a finger. The wall sensor reads the chest rising and keeps the waveform, so it can see the rhythm of your breathing, breath to breath, not just a number.
How cleanly the heartbeat pattern can be read from the chest. A trend no finger sensor produces. Investigational: shown as a wellness trend while research continues.
Body movement across the whole bed through the night: restless spells, turning, stillness. A ring knows what one hand did.
Bed presence is read directly. When you got up at 02:45 and for how long. When you woke, and when you actually got out of bed, which are not the same time.
Every night sits beside your own recent nights. In care settings that comparison has shown a change an average of 4 to 6 days before a diagnosis was recorded.
Plugged in once, on the wall, reading through the duvet. It is there on the nights you forgot the ring on the charger.
What the ring keeps doing better: daytime activity, heart-rate variability, skin temperature, sleep stages. Keep it on.



Two nights can average the same breaths per minute and feel nothing alike. The sensor keeps the spacing between breaths, not just the count.
Not how fast, how clearly. In Somily it is tracked against your own nights as a wellness trend.
| A smart ring | Kardian, on the wall | Read this with | |
|---|---|---|---|
| What it touches | Your finger, all day and all night. | Nothing. It reads through bedding from about 1.5 m away. | |
| How it senses | Light shone into the skin (photoplethysmography) reads blood-volume pulses; an accelerometer reads movement; a thermistor reads skin temperature. | Radio pulses at about 7.3 GHz reflect off the chest; the sensor reads the rise of each breath and the motion of each heartbeat. | Two different physical signals. Neither is an ECG. |
| Heart rate | Yes, day and night. The best-studied rings publish night-time heart-rate agreement with ECG that is very high. | Resting heart rate, at rest, from the chest motion. Carotid pulse rate agreed with ECG at 0.985 in the 2019 study; the current product is bench-checked to within 1.8 beats per minute. | Both good at rest. A ring also reads you walking; we do not. |
| Heart-rate variability | Yes. This is a ring strength. | No. We do not measure or report HRV. | If you use HRV, keep the ring. |
| Breathing rate | Estimated from the pulse signal. We could not find a published validation of ring breathing rate against a clinical reference. | Measured from the chest itself, with the breathing waveform kept. Agreement with a physician's count 0.852 in the 2019 study. | Breathing rate is the vital sign that moves first when something is wrong, and the one we were built for. |
| Breathing rhythm | Not reported. | The breathing waveform is kept, so the regularity of the rhythm from breath to breath can be followed as a wellness trend. | Wellness trend, not a diagnosis. |
| Heartbeat Clarity | Not reported. | A measure of how cleanly the heartbeat pattern can be read from the chest. Investigational; shown in Somily as a wellness trend. | Research is ongoing; it is not a claim. |
| Sleep stages | Yes: light, deep, REM. Published validations of the best-studied rings put four-stage agreement with the sleep lab in the mid-seventies per cent. | No. We do not stage sleep. We show time in bed, how settled the night was, and resting heart rate and breathing through it. | Staging agreement and a correlation coefficient are different quantities; do not rank them against each other. |
| Sleep apnea | Some wrist devices hold a screening clearance; rings generally do not. | Published research agreement with polysomnography (0.927, 94 adults). Not cleared; no Kardian product screens for apnea. | Neither is a diagnosis. |
| Body temperature | Yes, skin temperature trend. | No. | |
| Daytime activity | Yes: steps, workouts, readiness. | No. It reads the bedroom, and only while you are still. | |
| Change from your own baseline | Readiness-style summaries, as wellness. | Each night beside your own recent nights. In care settings this has shown a change an average of 4 to 6 days before a diagnosis was recorded (retrospective). | The care-setting record exists only on the radar side, because that is where the clinical device has been deployed since 2021. |
| Bed presence, bed exits | Inferred from wear and stillness. | Direct: occupied or vacant, when you left the bed at night and for how long, and the gap between waking and getting up. | Useful for a caregiver as much as for you. |
| Body movement | One hand. | Head to toe: how restless the whole body was, and when. | |
| Sharing with a care team | Consumer app; some offer family sharing. | XKare shares with a caregiver; the XK300 Essence feeds a care team through remote monitoring. | |
| Regulatory status | Generally wellness products. A few individual features on some wearables hold clearances in some markets. | XK300 and XK300 Essence: FDA-cleared for heart rate and breathing rate in adults, prescription. Kardian Somily: a wellness product. | Clearance is per measurement, not per device. |
| Upkeep | Charge it every few days. Take it off for some activities. Sizing matters. | Plug it in once. Nothing to wear, charge or remember. |
Anything that happens away from the bed: steps, workouts, daytime heart rate, HRV, skin temperature, and sleep staging. If those are what you use, nothing here replaces them.
Breathing rate measured from the chest with its waveform, resting heart rate with nothing worn, bed presence and movement, a nightly baseline that a care team can act on, and a clinical device with a certified outcome record behind it.
Keep the ring on. The radar adds the measurements a ring does not make, from a sensor you never have to charge or wear. Read both in the morning: the ring for how you slept and recovered, the radar for whether your breathing and resting heart rate look like your usual self.
Ring statements reflect the published validation work of leading ring makers and the peer-reviewed studies they cite. Radar statements are sourced on this page.
510(k) K202464, Vital Sign Monitoring Sensor XK300, cleared 26 April 2021. Class II. Product code DRT, cardiac monitor, 21 CFR 870.2300. Indications: measurement of heart rate and breathing rate in adults. Prescription use. Later radar vital-sign devices from other companies cite this clearance as their predicate.
Cleared in Canada, Australia, Singapore, Thailand and South Africa. The XK300 Essence shares the XK300's radar hardware and clearances; only the enclosure differs. Kardian Somily is sold as a wellness product and is not a medical device in any market.
Manufactured under an ISO 13485 quality management system, audited annually through the Medical Device Single Audit Program. Radio emissions within the indoor ultra-wideband rules of the FCC (Part 15), the EU (EN 302 065) and Canada (RSS-220). Radio certifications held: FCC (United States), ISED (Canada), CE / RED (European Union), MIC (Japan), KC (South Korea) and ACMA (Australia).
Listed in the WHO Compendium of Innovative Health Technologies for Low-Resource Settings, 2024, at technology readiness level 9. WHO's evidence assessment: "Recommended". Its clinical assessment: "Recommended with caution", noting that in an infectious-disease outbreak repeated patient contact for vital signs and the disinfection of shared equipment are problematic, so contactless monitoring can be advantageous, while blood pressure and temperature would need separate assessment and the device monitors one patient at a time. The entry also records that the manufacturer's submission lacked stated accuracy ranges, which is one reason this page exists.
 The WHO Compendium entryPage 62 of the 2024 Compendium: the XK300 listing and WHO's clinical assessment.
 Certificate of ValidationValidation Institute, June 2024. Signed by its Chief Data Scientist and Chief Executive.
 The published correctionScientific Reports, November 2024: the disclosure of the hardware source and co-founder affiliation.
Our data science team published its method in February 2026. Six outcomes, each with the number of cases, how often the model told cases from controls on data it had never seen, and how many days before the documented event the first alert came, on average.
| Health outcome | Cases seen | Model accuracy | Early notice |
|---|---|---|---|
| Hospital transfer | 510 | 76.5% | 5.5 days |
| End of life | 335 | 89.5% | 6.3 days |
| COVID-19 | 189 | 71.1% | 3.9 days |
| Urinary tract infection | 108 | 74.5% | 4.3 days |
| COPD exacerbation | 31 | 72.5% | 4.1 days |
| Heart failure | 28 | 73.2% | 5.3 days |
2,402 residents of 34 long-term care facilities in the United States, average age 78, monitored between 2022 and 2025: more than 22,300 days of data, 5.2 billion heart-rate and 9.6 billion breathing-rate readings, about 2,500 patient-years, and some 7,000 documented health outcomes.
From the facilities' electronic health records: admission, discharge and transfer events for hospital transfers and deaths, and structured ICD-10 primary diagnoses entered by licensed staff for infections and conditions. All data were anonymised before modelling.
Each outcome group was matched with an equal-sized control group from the same window. Models were trained on 80% of people and tested on the other 20%, repeated over random splits, with no person in both sets. Only sensor-derived features were used: no age, sex, diagnosis or medication inputs.
Retrospective, and drawn from one care setting in one country. Record timestamps can lag the true onset. Some controls may have had undocumented events, which makes the estimates conservative. The models are meant to flag patterns for a human to review, not to diagnose or to act on their own.
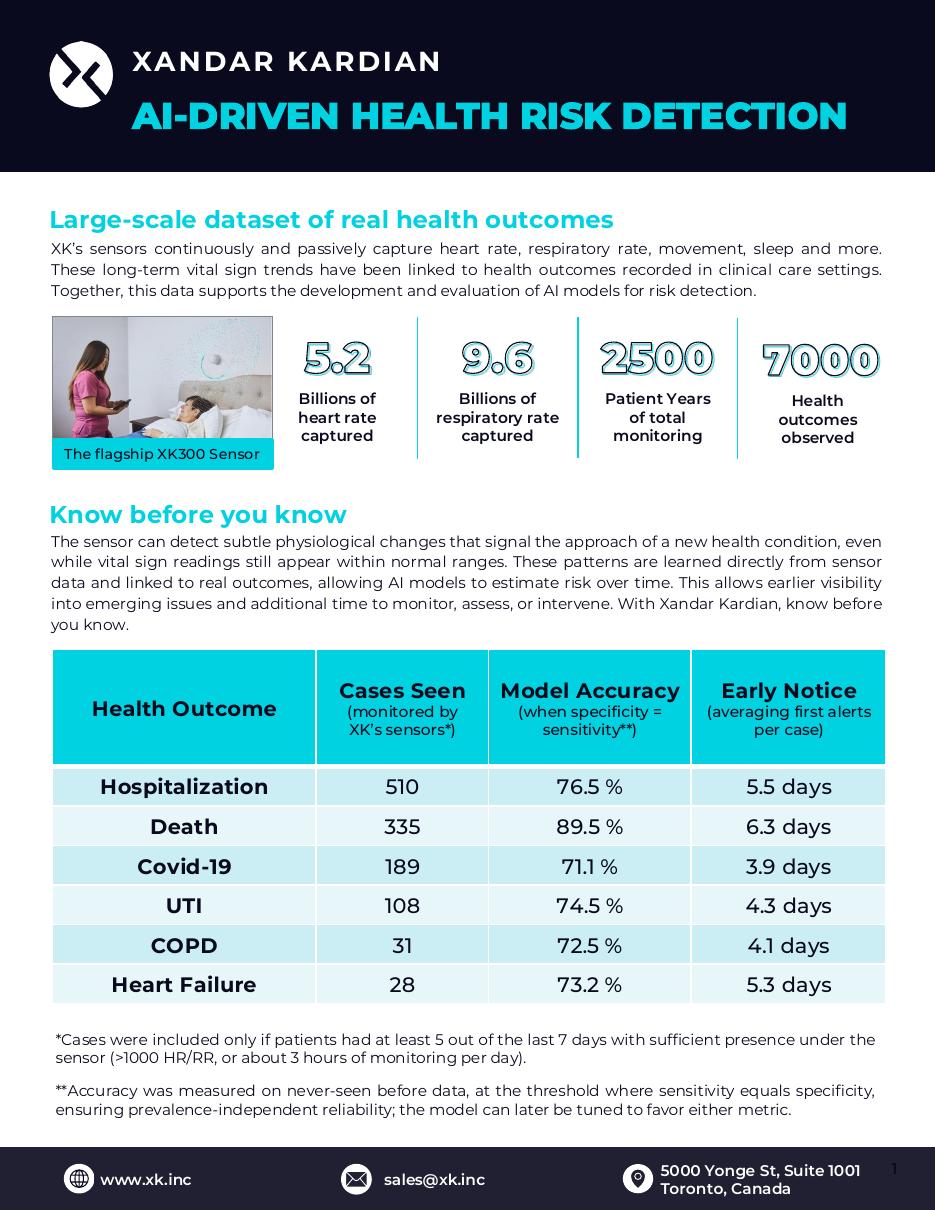 AI-driven health risk detectionPage 1: the dataset and the outcome table.
 Scientific methodology, 1Page 2: care setting, data collection, outcome identification.
 Scientific methodology, 2Page 3: study and control groups, training procedure.
 Scientific methodology, 3Page 4: the accuracy metric, lead time, study boundaries.
 Validation Report, 2024The Validation Institute's eleven-page review. Cover.
 The claim as submittedPage 4: what Xandar Kardian asserted and the Institute tested.
 Findings and validationPage 7: 75.6% of hospital transfers, up to seven days before, 201 patients.
 The COVID-19 protocol paperGerontology and Geriatric Medicine, 2024, in the PubMed Central open archive.
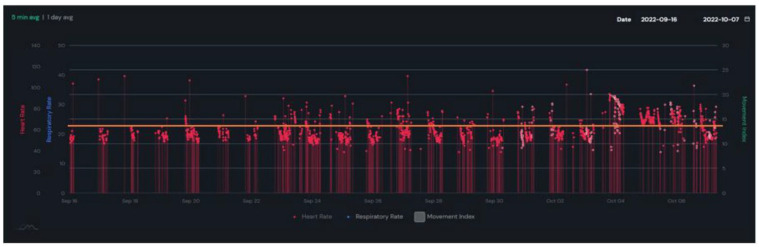
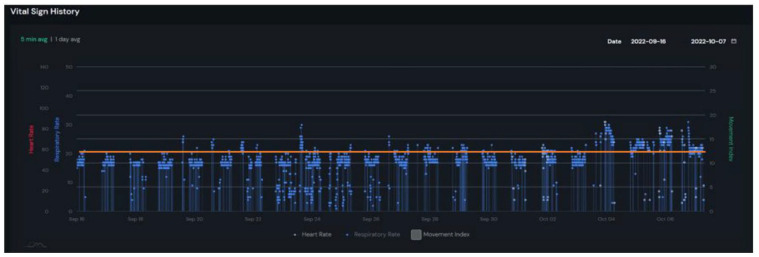
A measure of how cleanly the heartbeat pattern can be read from the radar signal. In our care-setting record, readings of 0.1 or lower have shown a strong association with the heartbeat patterns seen in heart failure. This is ongoing discovery. It is not a diagnosis, not a cleared claim, and it is shown in Somily only as a wellness trend.
Two threads. First, the care-setting record: in our February 2026 analysis, 28 documented heart-failure events, with the model telling cases from controls 73.2% of the time and a first alert on average 5.3 days before the record. Twenty-eight is a small number, and we say so. Second, Heartbeat Clarity readings of 0.1 or lower show a strong association with the heartbeat patterns seen in heart failure. A research programme with cardiology hospitals is in preparation, with ethics review before any patient is enrolled. Until it is published, everything about heart failure on this site is research, not a capability. In every one of the 28 events, Heartbeat Clarity had fallen to 0.1 or lower before the event was documented. A global clinical trial is under way. Shown as research, not as a claim.
The radar's agreement with polysomnography has been published, as described above. No Kardian product is cleared to screen for or diagnose sleep apnea, and none of them does.
We publish what we find, including when it is not what we hoped. Study designs are agreed with the hospitals before the data is collected. Company staff who co-author are disclosed. And a result stays labelled "research" until a regulator has reviewed it.
The radar inside Kardian products grew out of the laboratory of our co-founder, Professor Sung Ho Cho. His group and its collaborators have published on impulse-radio UWB radar for more than a decade. The papers most relevant to what our products measure are listed first, with links where the article is open.
 Scientific Reports, 2019Breathing rate and carotid pulse from one radar signal. Open access.
 Scientific Reports, 2020Sleep apnea against polysomnography, 94 adults. Open access.
Gerontology and Geriatric Medicine, 2024The COVID-19 early-detection protocol in a skilled nursing facility.
Thirty-six patents, nine of them granted in the United States and the rest in Korea, cover measuring vital signs, arrhythmia and sleep efficiency with radar, sleep-apnea detection, signal-quality checking, and the detection and counting of people. Among them: US 11,529,064 (measuring biometric signals by radar), US 11,426,120 (sleep efficiency by radar) and US 12,232,862 (sleep-apnea detection with IR-UWB radar).
Most of this work was done at a university, with public research funding, and reviewed by journals we do not control. Where company staff or our co-founder are authors, the papers say so, and so do we.
If you are a researcher and want the full list, a datasheet, or to discuss a study, write to us through the contact form. Ask XK-AI below can answer most technical questions from this page.
We do not publish how well the sensor tells light, deep and REM sleep apart, because we have not validated that against polysomnography. Sleep in our products is a wellness estimate from heart rate, breathing and movement.
The polysomnography study exists. A regulator has not reviewed it, and our products do not act on it.
Our ±1.8 beats-per-minute figure is checked under audit, but it has not been through a journal. We say "audited", not "proven".
The Validation Institute certification covers one operator's facilities and 201 admissions. It is the only third-party outcome check we hold. We would like more.
The accuracy studies ran for a session or a night, under supervision, mostly in younger adults. Months of unsupervised use at home is a different setting, for every device in this category.
The 4.3, 3.9 and 6.3 day averages look backwards at records. A prospective study, designed in advance, would be stronger evidence, and that is what the research programme above is for.
Datasheets, protocols, evidence packs and programme details live on our clinical site.